
Home Blog Page 39

The Show Must Go On

If you are a science writer in search of material, your best bet is to review a few of yesterdayโ€™s mainstream media pronouncements reporting government vaccine experts. You could find enough public misdirection to keep you writing for a week.

Among yesterdayโ€™s four Covid advice articles in Stuff โ€œKiwis suffering health issues after Covid-19 vaccination want to be heard, but it’s complicatedโ€ raised the art of mixed messaging and gaslighting to new heights.

It started off well, raising the case of someone in Wellington debilitated with pericarditis, unable to even go for a walk, hang up washing, or vacuum, but it rapidly went off the rails. The lady is described as anxious to get her booster for the good of the general public.

We were reassured by Stuff that the Accident Compensation Commission (ACC) insurance scheme had only accepted 987 claims for vaccine related injuries, a supposedly unconcerning rate of 0.009% of doses (possibly 50 times higher than any prior vaccine).

77 of these accepted ACC vaccine injury claims are for myopericarditis. The others were for other serious conditions. Then we were told there have actually been 783 people who have reported incidents of myopericarditis following vaccination to Medsafe.

In my book this implies that only 10% of myopericarditis claims have been approved by ACC. You didnโ€™t have to read far before Dr. Nikki Turner Director of the Auckland University Immunisation Advisory Centre weighed in with the advice that some adverse reactions to vaccination such as heart palpitations could be due to anxiety about needles.

These people should be treated with compassion, she said, (but presumably refused an insurance claim).

It gets worse, Dr. Sanjana Hattotuwa with his recently minted Ph.D., formerly a pro-democracy spokesperson from Sri Lanka, and now described by Stuff as an โ€˜independentโ€™ (?)ย researcher employed by the NZ Government-funded Disinformation Project, was quoted as describing people seeking compensation for vaccine injuries as having beenย instrumentalised by anti-vax groups.

He is quoted as telling Stuff that New Zealand is a high trust society involved in a broader struggle as it tries to get to grips with the erosion of social cohesion and trust. Something that our institutions have failed to keep up withโ€ฆThe culprits are anti-vax groups.

(Note the language: โ€˜broader struggleโ€™, โ€˜erosion of social cohesionโ€™, โ€˜culpritsโ€™, โ€ฆ., is Hattotuwa or Stuff actually talking about New Zealand here?)

โ€œ..I donโ€™t think the health agencies, institutions, and ministries fully appreciated the instrumentalisation of the content they were putting outโ€ Hattotuwa says.

In other words, Dr. Hattotuwa appears to be advising the government to put out less information about the pandemic in case it is misrepresentedโ€”a form of government censorship of scientific information.

Such statements no doubt could beย misconstruedย as encouraging our government to become a more secretive and authoritarian state. Is this our Kiwi futureโ€”I hope not.

Thank God that Dr. Nikki Turner disagreed:

โ€œIโ€™m very much in favour of us as a country learning how to do critical appraisal and understand science, not just assume that people canโ€™t figure it out.โ€

So why isnโ€™t Dr. Nikki Turner publicly debating vaccine safety? Instead in the article, she labelsย anti-vax misinformation as an industry that should be called out. So no public debate then, just a cancelling fest from the safety of an ivory tower.

Distinguished immunologist Dr. Graham Le Gros executive director of the Malaghan Institute and head of Vaccine Alliance Aotearoa told Stuff that:

โ€œNZ has a good system for reporting events possibly related to vaccinations and a high level of engagement from the public and healthcare professionalsโ€

Since my involvement with writing about the science of the pandemic, I have been writing to Government scientists calling for mandatory reporting of adverse events subsequent to vaccination as is normal in vaccine trials. Medsafe says that only 5% of events are reported in NZ. Dr. Ashley Bloomfield has specifically refused to countenance this step.

Dr. Le Gros makes my point for me, saying:

โ€œit will take ten years to assess all the risks of the vaccineโ€”as is the case with all new vaccinesโ€.

So have I missed something? We are rolling out to the public a vaccine using completely novel biotechnology the true extent of whose risks, we are assured by one of our most senior scientists, will not be known for ten years. Yet we will not be requiring mandatory reporting of adverse effects???

The article in Stuff fails NZ because it cherry picked examples of people suffering severe effects from myopericarditis and even one family of a teenager who tragically died, all of whom say the show must go onโ€”no one should be discouraged from vaccination.

The majority of the 706 (at least) people with myopericarditis who have not been given a voice or compensation might disagree.

Tomorrow I could look at the implications of the opinion piece in todayโ€™s Stuff which calls on Jacinda Ardern to virtually guarantee these admittedly risky and hugely ineffective vaccinations are taken by all New Zealanders right down to the very young.

How one wondersโ€”back to the coercive mandates whose supporting legislation Jacinda Ardern says she plans to keep in her back pocket?

Where Did the โ€˜Scienceโ€™ of the Pandemic Go Wrong and How to Put It Right?

A paper published on April 5th in the New England Journal of Medicine entitled โ€œProtection by a Fourth Dose of BNT162b2 against Omicron in Israelโ€ is raising eyebrows in the scientific world because of its deficiencies.

Dr. Vinay Prasad is an American hematologistoncologist and health researcher. He is an associate professor of Epidemiology and Biostatistics at the University of California, San Francisco. His work has coined the term medical reversal whereby more careful trials of a drug show that its earlier approval was flawed.

Dr. Prasad, who is not an anti vaxxer by any stretch of the imagination, has aired his concerns about the latest Israeli paper on Omicron and boosters in a YouTube video titled: Israeli Data for the 4th Dose | How Good Is It? | Make Bourla Earn His Pay.

In essence, Dr. Prasad is concerned that there is a potential for inherent bias as the group of subjects in the Israeli study who took the fourth booster was self-selected rather than randomly assigned.

In other words, he was asserting that any assessment of vaccine efficacy published in a leading journal like the NEJM should use the gold standard of scientific proof, rather than inferior methods known to allow confounding effects to creep in.

Dr. Prasad pointed to the current $100 billion of annual Pfizer revenue and asked: Why isnโ€™t Pfizer conducting randomised controlled trials to assess the efficacy and safety of boosters rather than applying political pressure to bypass scientific concerns? He said this was debasing scientific standards.

Dr. Prasad also pointed out that the actual data underpinning the results of the Israeli study were inconsistent with the known trajectory of immunity development and therefore with the studyโ€™s conclusions that the booster was helping.

So precisely how could self-selection in the Israeli study invalidate results? Dr. Prasad suggested one possible mechanism: those volunteering for fourth boosters might be more healthy individuals.

We ask: How could this happen? There are a number of ways.

For example, let us take seriously the commonly voiced proposal that the Covid-19 spike protein is essentially a toxin. A toxin capable of causing the heart and organ inflammation, neurological effects, and the potentially damaging immune system storm associated with both Covid infection and vaccination.

As with any toxin, some individuals will have greater and others lesser reactions to the toxin depending on a whole range of individual physiological circumstances.

As the series of inoculations proceeds from first to fourth jab, those individuals having a greater adverse reaction to the shots will be weeded out by self-selection. Those experiencing more unpleasant reactions to the spike protein toxin will naturally decide to forgo further injections as the vaccination series unfolds.

Since both the Covid virus and the vaccine expose the physiology to the spike protein which accounts for a significant part of the Covid aetiology and symptomatology, those more tolerant of the toxic effects of the spike protein will have lesser symptoms following Covid infection.

The net effect of this on the results of the Israeli study is clear, those volunteering to receive the fourth booster will appear to be gaining benefit from the booster because they have self-selected for greater tolerance.

As a result there will be a tendency to see a slightly lower rate of hospitalisation and death subsequent to receiving the booster, precisely the result of the Israeli study. As the efficacy of the booster on the viral component of Covid wanes this effect will dissipate.

Dr. Prasadโ€™s point is clear, the only way to sort out what is actually happening is to conduct a randomised controlled study where subjects are assigned to vaccination and the matched control group receives a placebo.

Pfizer has the money to do this. So why arenโ€™t they? Possibly because a randomised controlled trial may uncover some potentially serious issues for Pfizer.

Without a carefully designed randomised controlled study, results are subject to the vagaries and inconsistencies of national data collection policies:

  • Is Covid data collection mandatory, (in most countries including NZ it is not)?
  • How carefully are records kept?
  • How are Covid hospitalisations defined (for example are pregnant mothers in hospital to give birth who coincidentally test positive for Covid recorded as a Covid patient)?
  • How are Covid deaths recorded, how long after a positive test and whether they had other health conditions?

Letโ€™s look at the New Zealand current deaths data which illustrates these points:

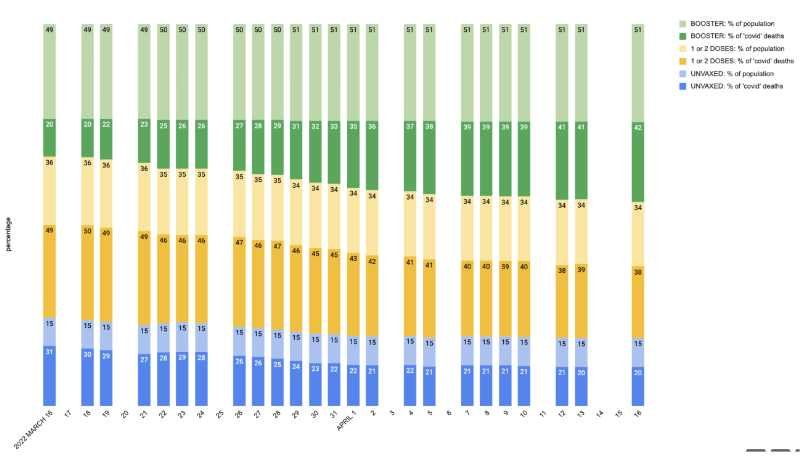
Proportion of covid deaths by vax status (dark colours) with Proportion of total population in each vax status (light shades)

Shows all deaths ASSOCIATED with covid: ie from any cause within 28 days of a + test. (Unfortunately, the MoH does not release the vax status of CONFIRMED covid deaths)

If you read this graph at face value you must conclude as follows:

During the last month boosted individuals have become more vulnerable to death from Covid that they were at the start. Both the vaccinated (excluding the boosted) and unvaccinated groups have become less vulnerable to death through Covid. The increasing vulnerability of the boosted group over time is consistent with the Israeli study. One possible interpretation of the figures is as follows:

The level of natural immunity (due to prior infection) is rising among the unvaccinated as a greater percentage of this group catch and recover from Covid, whereas the more mRNA injections you have had appear to inhibit the acquisition of natural immunity.

However few safe scientific conclusions can be drawn from this table. The New Zealand Ministry of Health does not release sufficient data and the numbers are small. We do not know how many of these deaths were with Covid and how many because of Covid in the various vaccination categories.

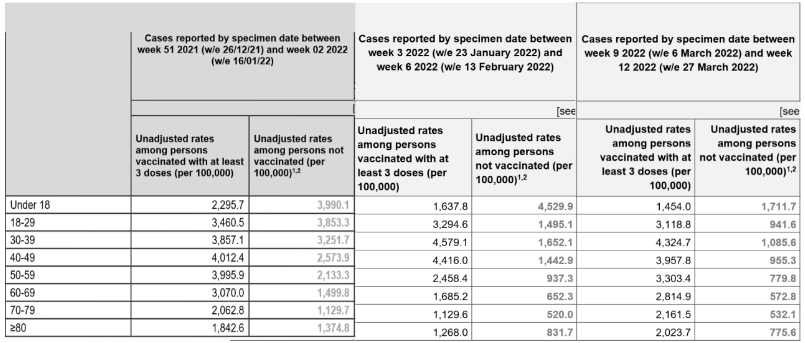
We can however segway to figures from the UKHSA. Up until the end of March the UKHSA conveniently provided the case-rates per 100,000 individuals by vaccination status in their vaccine surveillance reports, and the following table has been stitched together by online UK publication The Expose from the case-rate tables found in the Week 3, Week 7 and Week 13 Vaccine Surveillance Reports.

As you can see from the above, the case-rates per 100k have been highest among the triple vaccinated population over these 3 months, except for the 18-29-year-olds in the week 3 report only, and the under 18โ€™s in all 3 months.

However, as in New Zealand, the trend is clear: triple vaccinated individuals are becoming more vulnerable and not exhibiting the acquisition of natural immunity in every age category.

A sufficiently well planned and executed randomised controlled trial with a long duration would reveal what is going on, but neither Pfizer or government health agencies are moving in this direction.

In fact health agencies like the UKHSA are publishing less and less data, possibly because the data is suggesting alarming longer term health consequences of mRNA vaccination.

The lack of complete data at this point actually confounds the issue because it becomes increasingly difficult to sort out what adverse health effects of Covid are due to infection and which to vaccination. If the supposition that the spike protein is a toxin is right, both will have similar effects to varying degrees.

The action point is clear: mRNA vaccination is not working and could be dangerous. In the absence of reliable clinical assessment, and in the presence of concerning data, the use of mRNA vaccines should be paused.

This article is available to download: Where Did the โ€˜scienceโ€™ of the Pandemic Go Wrong and How to Put It Right? (PDF)

Message to NZ Mainstream Media and Scientistsโ€”Change is Coming

World media and government science advisors acknowledge the limitations of the regulatory process for mRNA vaccination.

We shouldnโ€™t understate the naivete of the New Zealand government, media, and scientists during the pandemic.

The tabloid-style stories of severe Covid outcomes, the authoritative voice of Dr. Anthony Fauci (who has financial conflicts of interest), the allure of the word vaccine, and the exaggerated death toll in foreign lands, all combined into a convincing call for immediate and coercive action.

Yet behind the stories, the highly profitable pharmaceutical PR system was running at full steam playing on the fear factor. New Zealand fell head over heels in love. Love knows no reason and that was certainly the case here.

New Zealand is a long way away from the rest of the world. We have a tradition of proud independence and self-sufficiency, but we rolled over and played follow the leader. 

No one in a position of influence struck a note of caution, especially not our Prime Minister.

We instituted the largest public borrowing program in New Zealand history and spent it on a US mega corporation with a poor safety record and a history of punitive malpractice judgements.

The government instituted saturation advertising of vaccine safety and efficacy, and then followed up with mandates, sackings and social exclusion. Our media shouted down those few asking questions.

Times Have Changed

The prestigious and conservative Wall Street Journal (WSJ) has aired concerns about poor regulatory decisions at the US Food and Drug Agency (FDA) about booster shots. They join a growing international chorus of highly qualified and influential voices.

On April 3rd in an opinion piece entitled โ€œFDA Shuts Out Its Own Experts in Authorizing Another Vaccine Boosterโ€ Dr. Marty Makary, a surgeon and public policy researcher at Johns Hopkins University School of Medicine writes:

โ€œThe FDA last week authorized Americans over 50 to get a fourth Covid vaccine dose. Some of the FDAโ€™s own experts disagreed, but the agency simply ignored them.โ€

Eric Rubin, editor in chief of the New England Journal of Medicine (arguably the worldโ€™s most influential medical journal) and a member of the FDA advisory committee on vaccines told CNN last month:

โ€œI havenโ€™t seen enough data to determine whether anyone needs a fourth doseโ€.

Dr. Cody Meissner, also a member of the FDA vaccine advisory committee and chief of pediatric infectious diseases at Tufts Childrenโ€™s Hospital agreed saying:

โ€œthe fourth dose is an unanswered question for people with a normal immune systemโ€

A third member of the committee, Dr. Paul Offit of the Childrenโ€™s Hospital of Philadelphia went further. He told the Atlantic magazine that he advised his 20-something son to forgo the first booster.

The WSJ article described the effect of boosters as fleeting, mild, and short-lived.

Two top FDA officials, Marion Gruber, Director of the FDA Office of Vaccine Research and Review and her deputy Paul Krause, quit the FDA in September last year complaining of undue pressure to authorize boosters and a lack of data to support their use.

Unbelievably, the US Centre for Disease Control (CDC) rubber stamped the FDA decision to approve a second booster without even convening its panel of external independent vaccine experts.

Safety Testing of mRNA Vaccines is Inadequate, Incomplete, and Biased

The Wall Street Journal article sounded a note of alarm saying that neither the CDC nor the US National Institute of Health (NIH) had made a priority of studying vaccine complications.

Moreover, their VAERS data collection and analysis process is incomplete and inadequate. In other words, the safety investigation to date of adverse effects of mRNA vaccination is incomplete and potentially misleading.

The central question raised by the Wall Street Journal opinion piece is why wouldnโ€™t the US regulators wish to undertake accurate and complete investigation of adverse effects of mRNA vaccination?

Have pharmaceutical interests been able to influence decision-making at the FDA to their own commercial advantage at the expense of safety considerations?

A leading authority the British Medical Journal agrees, on March 16 it published an article entitled The illusion of evidence based medicine in which it said:

โ€œEvidence based medicine has been corrupted by corporate interests, failed regulation, and commercialisation of academia.โ€

The Lessons For NZ Are Obvious

We have stifled debate and slavishly followed FDA advice. Now there is a need for reevaluation and debate. We have travelled a long way down a one way street, but it appears to be a dead end.

The triumphant articles published about a survey of vaccine resistant people born in Dunedin was a low point in uncritical NZ mainstream media publishing. We have to regain an objective voice.

Aย paperย published on April 5th in the New England Journal of Medicine found that any measurable protective effect of the fourth inoculation (which in any case, it found, is very small in absolute terms) disappeared after just 8 weeks.

Moreover, aย paperย in the Lancet on April 8th admits that boosters carry a risk of additional side effects.

Both these papers skirted the obvious safety questions in favour of weak praise for vaccine orthodoxy. In contrast, the Wall Street Journal article asked the important question:

Who is actually getting serious about measuring the extent of adverse events, rather than continuing to urge uncritical acceptance of a largely ineffective vaccine?

So far New Zealand media have steered clear of questions. Dr. Ashley Bloomfield has refused to institute mandatory reporting of adverse events following mRNA Covid vaccination and he has excelled at denying vaccine exemptions to those injured by the first shot.

Silence is no longer tenable, in actuality it never was. Questions have to be asked. No ifs or buts. Overseas media outlets of the thinking kind are waking up.

If we canโ€™t face debating rationally with our critics, we are a nation drifting onto the rocks of ignorance and prejudice.

Time for us to wake up.

The Long Readโ€”Misinformation and Lack of Information Distort Reality

Is there a myocarditis time bomb affecting athletes or is it disinformation?

Are anti vaxxers ignorant people who suffered childhood abuse?

Adverse effects of mRNA Covid vaccination affecting athletes is not a sacred cow in the fact checking world.

Throughout 2021, multiple attempts were made to debunk persistent reports that an unusual number of athletes were suffering cardiac events that might be related to mRNA Covid vaccination.

The main theme of these fact checking efforts was denialโ€”athletes were not at risk and cardiac events were not happening.

In 2022 this dialogue is evolving because the numbers are growing and harder to ignore. According to an investigative report by OAN, a pro-Trump online US news site, 769 athletes suffered sudden health events between March 2021 and March 2022 with an average age of 23 years.

For example in February, fifteen despairing players withdrew from the Miami Open. Yes, that is 15 in one tournament. No doubt anti-vaxxers who were locked out of most sporting events, whether they were participants or spectators, during 2021 called out from the parking lot thank goodness some people are still counting.

Of necessity in the face of mounting numbers of injury reports, the fact checking dialogue has hesitated on the brink, but on February 1st of this year, the Washington Post still labelled stories of adverse effects of mRNA vaccines on athletes FALSE.

Their story relied heavily on a discussion of a single Danish footballer Christian Eriksen who suffered a cardiac arrest on June 12 2021 just before half time. The circulation of the apparently false story that Eriksen had been vaccinated was attributed by the Washington Post to a shady far right group in Austria seeking to influence their upcoming election. The pro-vaxxers cheered from the stands.

Dig deeper and the story gets more murky. Few if any of the participants in this argument on both sides have verified hard facts to hand. There are a number of people making strong statements based on the certainty of belief.

The Washington Post, who had probably realised by February that it was quite possible that an unusual number of athletes were unexpectedly falling to the ground, decided to finish its article by asserting that the sporting collapses must be due to Covid not Covid vaccination. Again no hard facts about actual athletes, just a polarised muck throwing event.

Data Collection Is the Right Way Out of This Counterfactual Maze

As a scientist, I realise that what is lacking here is reliable data. Why is it lacking? Here is the nub, the authorities are so sure they are right about the safety of vaccines, that they are refusing to collect data.

New Zealand has refused to institute mandatory reporting of adverse events following mRNA vaccination and other countries are in the same boat. We donโ€™t have a lot of data to go on because it is not being collected. Sporting bodies are not counting either, or perhaps they have lost count or looked the other way.

Delving into the world of psychology, I can only find this unsettling. Why wouldnโ€™t we collect data? Why arenโ€™t we allowed to ask questions without being shown a red card? Why isnโ€™t the Ministry of Health counting and publishing up to date medical data on the frequency of cardiac and thrombotic events of all types?

There are stories in the popular press (actually not so popular these days) reporting recent excess cardiac events as due to โ€˜holiday heart syndromeโ€™ or the need for young people โ€˜to avoid strenuous exerciseโ€™. Neither of these had been a thing until 2021. Why havenโ€™t the MoH quashed these speculative sallies into obfuscation by publishing data? You tell me.

Are the Vaccine Hesitant in Dunedin Victims of Child Abuse?

The finger-pointing gets worse. One particular โ€˜wack-an-antivaxxerโ€™ sport recently originated at Otago Medical School. A popular digest of a study of 1,000 people born in Dunedin, NZ in 1972 was reprinted in leading publications around the world.

The article implied that anti-vaxxers suffered from sexual abuse, maltreatment, deprivation or neglect, or having an alcoholic parent as they were growing up. They were also described as low educational achievers likely to suffer from mental illness.

I am a little sceptical by nature, so I noticed that the reports in the popular press were based on an article in a publication called The Conversation, which has received support during the pandemic from the Bill and Melinda Gates Foundation.

The Conversation describes itself as both devoted to academic rigour and seeking to explain science to the general public. Curiously their article about the Dunedin survey only contained a single quantitative piece of informationโ€”13% of the respondents were vaccine resistant.

No other quantitative information was provided to support the extreme characterisation of the vaccine hesitant in the article.

I tracked down the actualย studyย entitledย โ€œDeep-seated psychological histories of COVID-19 vaccine hesitance and resistanceโ€. Seven of the ten authors were based in the USA. One of the authors disclosed that he is funded by the US CDC.

The survey completed in April 2021 actually found that 13% of the respondents were vaccine resistant and 12% were vaccine hesitant. So fully 25% of the respondents were vaccine hesitant to varying degrees.

I then rapidly came across an old friend used to distort information: absolute differences versus relative differences.

Of those willing to vaccinate (note the word used is willing, not necessarily keen), 62% had at least one Adverse Childhood Event (ACE). Of those hesitant or resistant to vaccination 73% had at least one ACE. 62% vs 73% is not a large difference in absolute terms.

Based on this small difference, Professor Richie Poulton, a Dunedin-based co-author of the study was quoted in the Otago Daily Times as saying about the vaccine hesitant and resistant responders:

โ€œThe childhood experiences of those surveyed ranged from sexual abuse, parental neglect, poverty, to isolation and lack of achievement in school. They covered the whole suite of difficulties you can think of that might impinge on a person’s good development. Their personality became … very stress reactive – they saw danger or threat where there essentially was noneโ€.

Now you probably did percentages at school, do you think Professor Poultonโ€™s comments accurately reflect the difference between 62% and 73% exposures to at least one ACE? Because I certainly donโ€™t. A significant percentage of both groups experienced ACEs growing up, but they had different opinions about vaccination.

Wouldnโ€™t it be more productive to ask: why do we have such a high rate of ACEs in NZ? Is our mental health service under funded? Is our education system failing us? Is support for families sufficient?

I went further down the pages examining results of a battery of โ€˜questionairesโ€™. I found that although there were measurable differences between the two groups: โ€˜vaccine willingโ€™ and โ€˜vaccine hesitant and resistantโ€™, their average scores were well within the standard deviation of the mean standardized score for each test.

This means most people responding to the survey were actually relatively average people. The vaccine hesitant and resistant were being falsely characterised as ill-educated social deviants. This sounds like victim blaming. So much for the academic rigour and capacity to explain science that The Conversation proudly aspires to.

Unpicking the Messaging is Really Important Here. It involves psychological manipulation

You can see where I am coming from canโ€™t you? Were the media comments about the study an unsupported and false attempt to discredit the unvaccinated and categorise them as outcasts and misfits without the necessary intelligence to think for themselves?

The small differences between the two groups were insufficient to justify this black and white condemnation widely shared around the worldโ€™s media.

There were some differences in educational attainment. 35% of the vaccine willing had a BA degree or higher. 15% of the vaccine hesitant or resistant had a BA or higher.

However, the Dunedin results may be misleading regarding the influence of education. A study in the USA found that people with a PhD were more likely to be vaccine hesitant, implying that a decision to not vaccinate may possibly be encouraged by the development of high level critical thinking.

In the mainstream media articles, Professor Poulton pleaded with us to feel pity for the unvaccinated, because of their supposed difficult childhood (which was in fact not so different from that of the vaccinated).

Was he simply lowering our opinion of the unvaccinated by playing upon stereotypes? Subtly hammering home the current NZ mainstream media messaging that only right wing extremists and selfish antisocials remain unvaccinated.

Did he realise that the unvaccinated are legitimately concerned about the vaccinated because they have been unwittingly exposed to serious but as yet unquantified medical risk?

As I am aware that Covid mRNA vaccine adverse events are running at 30-50 times higher than any previous vaccine, I would ask different questions of the data:

  • Were those willing to be vaccinated being misled by the inadequate content of their education?
  • Do prior adverse experiences provide good reason to be more cautious in future?

What do you think?

The Immunisation Advisory Centre at the prestigious University of Auckland (incidentally partly funded by pro-vaccine interests) reassuringly says:

โ€œConfirmed cases of myocarditis are rareโ€ฆMore than 80% of reported cases of myocarditis following mRNA Covid vaccination have recovered quickly with rest and commonly used oral anti-inflammatory medications such as ibuprofen.โ€

Are you reassured by this, or have you looked at the Medsafe adverse event data where 18,000 mRNA vaccine recipients reported chest pain and shortness of breathโ€”symptoms admitted by the Immunisation Advisory Centre to be indicative of myocarditis?

Have you concluded, like me, that as many as 80% of cases of myocarditis among the vaccinated remain unreported and untreated? A ticking time bomb, of which professional athletes represent only the tip of the iceberg.

Bickering without accurate data is a waste of time. If you refuse to look, you will never see.

The question is how long are our health authorities going to continue to look the other way and refuse to start counting accurately, appropriately, and retrospectively?

How long before government and media messaging becomes respectful and objective?

Does Covid-19 Contain Genetic Sequences From Snake Venom?

0

An article in Scientific American back in January 2020 reported:

โ€œSnakesโ€”the Chinese krait and the Chinese cobraโ€”may be the original source of the newly discovered coronavirus that has triggered an outbreak of a deadly infectious respiratory illness in China this winter.โ€

The article originated from a Chinese authored paper published in the Journal of Medical Virology on 22 January 2020 entitled Cross-species transmission of the newly identified coronavirus 2019-nCoV and said:

Our findings suggest that 2019-nCoV has most similar genetic information with bat coronavirus and most similar codon usage bias with snake.

The essence of the article was the supposition that Covid-19 made its way from snakes to bats and then to the Wuhan wet market, expressed as follows:

โ€œAn origin-unknown homologous recombination may have occurred within the spike glycoprotein of the 2019-nCoVโ€ฆ.The squared euclidean distance indicates that the 2019-nCoV and snakes from China have the highest similarity in synonymous codon usage bias compared to those of bat, bird, Marmota, human, Manis, and hedgehogโ€

This idea subsequently gained little traction, because of the improbability of such a train of interspecies transfer, and because public discussion of its conclusions was vigorously suppressed by fact checkers.

The suggestion of the authors to do more research disappeared from view. It has been largely forgotten until now.

Were Some of These Recombined Genetic Sequences From Snakes?

Recent discussion of the origin of the Covid-19 spike protein has suggested that it could be the result of recombinant techniques in the laboratory which joined a number of genetic sequences together as part of research to develop deadly pathogens, and then investigate possible cures.

A paper published in F1000Research entitled โ€œToxin-like peptides in plasma, urine, and faecal samples from COVID-19 patientsโ€ in April 2020 concluded that:

โ€œThe presence of toxin-like peptidesโ€ฆsuggests a possible association between COVID-19 disease and the release in the body of (oligo-)peptides almost identical to toxic components of venoms from animalsโ€ฆ.The presence of these peptides opens new scenarios on the aetiology of the COVID-19 clinical symptoms observed up to now, including neurological manifestations.โ€

What are Some of the Neurological Effects of Snake Venom?

A study published in 2002 entitled โ€œCardiac Involvement in Snake Biteโ€ reports:

โ€œMyocardial involvement is seen on occasions and may rarely contribute to morbidity and mortality. ECG changes are usually transient but when persistent they are attributed to direct myocardial damage due to the toxin.โ€

Other reported neurological effects of snake bite include:

  • pro and anticoagulant activity leading to ischemic or hemorrhagic stroke,
  • muscle paralysis through inhibition of neuromuscular transmission leading to respiratory failure.

All of these neurological, thrombotic, and cardiac effects are similar to reported adverse effects of both Covid infection and mRNA vaccination.

Is Covid-19 a Recombination of a Virus and a Toxin?

mRNA vaccines specifically train the human physiology to produce the suspect spike protein. Did this expose vaccine recipients to a toxin? It appears this might be the case.

In which case, the essential design of the mRNA vaccine would have been a grave error. It was training the physiology to produce a toxin.

These discussions are speculative. We now know that early genetic sequences of Covid-19 appear to have been suppressed by NIH on the instructions of the Wuhan Virology Lab.

Was the genetic similarity between snake genetics and Covid-19 too explosive to admit, whether they came from snakes or not? Certainly, this possibility should have been investigated vigorously.

It might have led to an understanding of the origins of Covid, but more importantly, it might have led to more effective treatments for Covid.

It might also have shed light on the source of the wide range of neurotoxic effects of both Covid and mRNA vaccination.

Whatever the eventual conclusion of further investigative research: biotechnology experimentation to research and develop pathogens and toxins must stop now. It amounts to a ticking time bomb.

Is Our Knowledge of Genetics Too Primitive to Edit Human DNA With Safety?

0

An investigation undertaken by Vanity Fair has revisited the origins of the pandemic and uncovered new findings.

In mid-2021 it came to light that key genetic sequences which might shed light on the origins of the Covid virus had been deleted by NIH at the request of the Wuhan Virology Lab. Administrators at NIH then sought to hide this revelation.

You can read the full articleย here:
This Shouldnโ€™t Happenโ€: Inside the Virus-Hunting Nonprofit at the Center of the Lab-Leak Controversy

If, as seems increasingly likely, both Covid and mRNA vaccines were produced by research biotechnologists, regulation has failed miserably. The conclusion is obvious, genetic experimentation on human genetic structures and deadly pathogens should be paused, period, not encouraged as is now being proposed. The ozone level was not protected from CFCs until they were banned outright.

My point in writing today is not to rehash the safety arguments around Covid origins that we have already covered several times in the Hatchard Report, but to say that there is a wide field of foundational research and exciting inter-disciplinary investigation in other fields that remains to be undertaken.

Mind/Body Systems Extend Throughout the Physiology

Physiological systems are both specific and non-specific, they are both localised and extended throughout the physiologyโ€”the whole is more than the sum of the parts. Human physiology is a system which works as a whole underpinned by genetic intelligence. Uniquely it combines biological structures and higher human consciousness.

We tend to erroneously believe that wisdom can be reduced to a series of rational choices taken much like the operation of a computer which completes yes/no binary operations so rapidly it can give the false impression of independent thought. Computers are not creative in the sense that we are, they are controlled by a limited set of instructions.

Neuroscientists (Meeks and Jeste, 2009) have proposed that in order to understand individual differences in wisdom, one also ought to consider multiple aspects of human brain physiology including its genetic structure.

For example, several genetic studies have reported that the heritability of prosocial behaviors, including altruism, is 50% to 60%. The heritability of impulsivity is approximately 45%. Complex brain processes involving multiple structures and neurological networks guide reflectiontoleranceemotions, and the ability to deal with ambiguity and uncertainty.

Your Heart Thinks for Others as Well as Yourself

In April 2016 aย studyย was published in Frontiers of Behavioural Neuroscience entitledย โ€œA Heart and A Mind: Self-distancing Facilitates the Association Between Heart Rate Variability, and Wise Reasoningโ€ย which extended these findings to include other physiological structures and communication between physiological systems. The authors found that varying heart rate (HRV) was related to balanced moral reasoning:

โ€œHRV indicators were positively related to prevalence of wisdom-related reasoning (e.g., prevalence of recognition of limits of oneโ€™s knowledge, recognition that the world is in flux/change, consideration of othersโ€™ opinions and search for an integration of these opinions) and to balanced vs. biased attributionsโ€ฆโ€.

The research suggests that wisdom-related judgments are not exclusively an isolated function of small units of the brain. They fall into the category of large coherent systems involving both mind and body. I canโ€™t emphasise enough how little is known about how these systems work and what key genetic structures they rely upon.

Long Range Coherent Systems Characterise Human Intelligence

Coherent phenomena are well known in physics. Remarkable properties result from extreme cooperation between identical atoms or molecules over extended distances.

For example, supercooled liquid helium undergoes a phase transition at 2.17 degrees Kelvin whereby all the helium atoms participate in a single superfluid state which is able to defy gravity and friction. Coherent structures may be associated with human consciousness.

Studiesย have found extended cooperative activity of neurons as a result of meditation as measured by phase coherence of EEG brain waves. This has been associated with a number of factors characteristic of higher human reasoning.

These include:

  • creativity
  • IQ
  • moral reasoning
  • concept learning
  • academic achievement
  • decreased neuroticism
  • and transcendence referred to by Freud and Romain as the โ€˜oceanic feelingโ€™โ€”being at one with the world as a whole.

In 1972 I attended a conference held at Queens University in Canada where Hans Selye, the inventor of the modern concept ofย stress, spoke. Dr. Selye defined stress asย the nonspecific response of the body to any demand placed upon it.ย 

He was talking about the intimate relationship between the generalised properties of our physiology and our psychological response to experiences. He pointed out that people who are under stress, have something overt in common, they all look illโ€”their whole physiology is involved with a psychological response to stress.

Our sense of Self, of being a whole person, of being protected even, is related to our whole physiology. The integrity of the physiology is maintained by homeostatic mechanisms and importantly by the immune system. The immune system is constantly in action performing more than a hundred quadrillion protective actions a day to maintain the integrity of DNA, cells, organs, and organ systems.

Thus our sense of self and safety, which confers a certain conscious freedom from fear and anxiety, is dependent upon and intimately connected to the operation of the physical immune system.

Unanswered Questions Point to a Pause in Genetic Experimentation

Does global cooperation between identical genetic structures in every one of the trillions of cells in the body give rise to coherent functioning of the entire physiology. Thereby supporting our stable sense of Self and higher wisdom?

Theย Heart and Mindย study points to the involvement of the whole physiology in moral human reasoning and that must also include our genetics. This leads to a number of topical questions that have not yet been investigated, let alone answered.

  • Long Covid and adverse effects of mRNA vaccination have both been associated with brain fog. As they both affect the function of the heart, could cardiac dysfunction contribute to a reduced capacity for mental acuity and emotional empathy? Mind and body are intimately connected, each affecting the other.
  • Several commentators have noted the prevalence of anxiety states, polarisation, scapegoating, and biased judgements during the pandemic among individuals, and networks of individuals and organisations. Are these due to the uncertainties of the pandemic or are there contributing physiological deficits?
  • Is the efficient functioning of our immune system integral to our sense of personal security? If either Covid infection or mRNA Covid vaccines reprogramme our genetic-based immune response to pathogens, would they interfere with the extended coherent structures that underpin our sense of well being and security?

We have no immediate experimental findings to answer these speculative neurological, psychological, and physiologicalย questions, but we should continue to investigate the propositions.

As we have few if any answers to the broad questions of genetic function, there are compelling reasons for extreme caution with medical genetic intervention.

Genetic alterations are passed down generations indefinitely where the consequences of mistakes will continue to reverberate (watch Dr. Peter McCullough succinctly highlights this pointย here).

Exclusive reliance on mRNA vaccine technology is increasingly looking like a cul de sac, and more probably a deadly trap.

Read previous Hatchard Report articles on this topic:

Guy Hatchard Ph.D. was formerly a senior manager at Genetic ID a global food safety testing and certification company (now known as FoodChain ID)

Guy is the author ofย Discovering and Defending Your DNA Diet

Stay Calm, and Stop Pressing the Pandemic Button

0

If you look at data from around the world, one thing is absolutely clearโ€”the Pfizer Covid mRNA vaccine has gone on strike. It is not working anymore.

Whether this should be described as due to variant mutation, waning vaccine efficiency, or forms of vaccine-induced immune system dysfunction is not definitively understood.

There is no statistically clear protective effect of Covid vaccination

However you canโ€™t argue against the dataโ€”there is no statistically clear protective effect of Covid vaccination in those highly vaccinated countries who publish complete records. The vaccinated are as likely to catch or be hospitalized with Covid as the unvaccinated.

Populations Have Become Polarised

Yet we remain in a state of social tension. Populations have become highly polarised and the level of fear is still elevated. Moreover, there is a measure of dysfunction that is gripping health services.

A friend of mine with a history of serious heart attacks called an ambulance over the weekend as symptoms recurred and was told that there would be a 7-8 hour wait. So off to the local GP.

The duty nurse, rather than immediately addressing the cardiac event, obsessed about Covid and vaccination. She insisted on Covid testing as the first priority. This is a metaphor for our current situationโ€”the pandemic is controlling our health services to the exclusion of other health care priorities.

Who can remedy the situation?ย The government and the media need to come clean and inform the population (and front line medical workers) that vaccinated or unvaccinated we are now all in the same boat, but they appear stuck and unable to change course.

There are a lot of lessons here. Governments have fallen into the hands of health professionals who have a narrow vision. In this one-sided situation, mistakes can be made.

Ineffective Medical Interventions Have Been Prioritised

In the UK this week, Ofsted, the education regulator, reported that mask wearing has affected the development of the young. Infants are experiencing difficulty acquiring language, social, and behavioural skills at the expected ages.

The problem lies with reduced exposure to facial cues because of mask wearing. Yet at a press conference this week in New Zealand, Dr. Caroline McElnay, retiring director of public health, expressed satisfaction that New Zealanders had become so acclimatised to mask wearing, that she expected thisย obviously beneficialย practice would continue into the distant future.

Studies show mask wearing is actually not very beneficial

Studies show mask wearing is actually not very beneficial. It does little if anything to reduce disease transmission, decreases vital oxygen levels in the lungs, increases bacterial colonies in the airways, and as we have just seen impairs educational and social interaction.

Mask wearing, like mRNA vaccination, has passed its sell by date.

Leadership Requires a Balanced Perspective

If you have ever been in a leadership position, you will realise that leaders come under a variety of pressures from various interest groups and individuals in any organisation.

The skill of leadership requires that you balance these pressures and stay ahead of those who are jockeying for position and influence, whilst ensuring that organisational achievement is maximised.

The government is currently heavily under the control of medical advisors who may not be taking a balanced view of priorities due to the heavily promoted myth of mRNA vaccinationย successย and the consequent scientific bias.

The government certainly achieved a large measure of protection early on by closing our borders and instituting isolation and track and trace policies.

The switch to policies based on vaccination rates, social distancing, and masking has not replicated these early results, but the public is unaware of the fundamental weakness of these policies.

To diffuse social divisions and fears, the government must speak out with a more balanced perspective. To reach a position of objective assessment they may have to first distance themselves from their close pandemic partners including the pharmaceutical biotech lobby which has greatly influenced health service professionals.

This biotech lobby has gained greatly in power during the pandemic, but their influence is more based on public relations and financial incentives than research findings. In contrast, actual research has not shown mRNA technology to be particularly effective or safe.

The Medical and Research Establishment Has Become a Target of Pharmaceutical Companies

You may doubt that the pharmaceutical lobby can influence the scientific and medical authorities, but they actually have a big reach in many directions.

Last month the prestigious British Medical Journal published an article on 16 March 2022 entitledย The Illusion of Evidence Based Medicineย saying:ย 

โ€œEvidence based medicine has been corrupted by corporate interests, failed regulation, and commercialisation of academiaโ€.ย 

It continued:

โ€œThe advent of evidence based medicine was a paradigm shift intended to provide a solid scientific foundation for medicine. The validity of this new paradigm, however, depends on reliable data from clinical trials, most of which are conducted by the pharmaceutical industry and reported in the names of senior academics. The release into the public domain of previously confidential pharmaceutical industry documents has given the medical community valuable insight into the degree to which industry sponsored clinical trials are misrepresented. Until this problem is corrected, evidence based medicine will remain an illusion“.

Indeed the BMJ has previous revealed deficiencies in the Pfizer mRNA vaccine trials.

โ€œโ€ฆ.the unintended, long term consequences for medicine have been severe. Scientific progress is thwarted by the ownership of data and knowledge because industry suppresses negative trial results, fails to report adverse events, and does not share raw data with the academic research community. Patients die because of the adverse impact of commercial interests on the research agenda, universities, and regulators.โ€

The article goes on to say that university administration has become dominated by academic managers and fundraisers whose priorities tend towards alliances with sources of funding and prestige, such as pharmaceutical companies and their satellite offshoots.

โ€œAlthough universities have always been elite institutions prone to influence through endowments, they have long laid claim to being guardians of truth and the moral conscience of society. But in the face of inadequate government funding, they have adopted a neo-liberal market approach, actively seeking pharmaceutical funding on commercial terms. As a result, university departments become instruments of industry: through company control of the research agenda and ghostwriting of medical journal articles and continuing medical education, academics become agents for the promotion of commercial products.โ€

Since the late 1990s the international development community began to encourage more active cooperation between the private and public sector in the form of public-private partnerships.

Here in New Zealand, the University of Auckland is a member of the Global Alliance of Vaccines and Immunization (GAVI Alliance), a public-private partnership.

Since its launch, the GAVI Alliance has been mobilizing funds from private and public donors and engaging United Nations agencies in partnership with pharmaceutical companies.

In 2005 under the GAVI Alliance supervision, a new initiative known as the Advance Market Commitment (AMC) started an innovative financing (cash prize) model for incentivizing new vaccine research and development.

The pharmaceutical industry also supports medical lobbyists out to influence politicians and government departments, some of whose activity is hidden behind shell companies whose links are hard to identify.

Pharmaceutical companies are also closely allied with drug regulators and international advisory bodies to whom they provide information, financial and logistical support.

Some lobbying is directed towards the public. In 2020 more than 75% of television advertising revenue in the USA came from the drug industry amounting to $5 billion. This year Pfizer proudly sponsored the Oscars.

Informed Voices Have Been Silenced

These links and influences are growing, funded by massive pharmaceutical profits during the pandemic. They call into question the validity of much pro mRNA vaccine rhetoric which is being paraded around by some government advisors. These biased assessments have been used to marginalise independent voices raising concerns.

It is time to stop labelling people who have raised questions about mRNA vaccination as anti-science, anti-social, and dangerous. These labels are entirely misplaced.

The safety and efficacy of mRNA vaccination is a scientific matter under continuing investigation. Doubters have already been validated by very disappointing outcomes. This needs to be openly acknowledged.

Moreover, there is more ahead. The extent of the safety downside of universal mRNA vaccination programmes is still the subject of further research efforts whose final outcome is unknown at this point.

Every day that goes by as governments continue to bury the ineffectiveness of mRNA vaccination through incomplete data reporting and deliberate evasion is a day that adds to social divisions and misinformation.

The longer it goes on, the harder it will become to dissolve the fault lines in society. There will be a point of no return and we have almost reached it.


The Hatchard Report receives no independent funding, our team are all volunteers. However, there are inevitable costs associated with running a secure website and mailing list. We depend on our readers to help us, either with monthly or one-off payments >>> Ways You Can Support Hatchard Report

Has the Ministry of Health Lost The Ability to Count?

Almost every day the Ministry of Health holds a live press briefing at 1 pm to announce the daily Covid statistics.

Yesterday was the 300th briefing of the pandemic, lovingly referred to as the โ€˜Podium of Truthโ€™ to honour the Ardern dictum that the government should be your only source of truth. 

Presumably most mainstream media outlets send along their junior stringer to record the information which is then duly reported to us plebs who missed the live broadcast. This is usually the leading story of the afternoon online editions and radio news bulletins.

The surge in Omicron infections, hospitalisations, and a mild sprinkling of deaths has enabled the current briefings to gain the added macabre interest of a Hammer horror film production.

Two days ago, I treated myself to the spectacle, because both Dr. Ashley Bloomfield, the Director General of Health, and Dr. Caroline McElnay, Director of Public Health were announcing their resignations.

In the event, neither of them provided any reason for their departure but duly congratulated each other on being jolly good fellows. The interesting part of the briefing was hidden away in their daily Covid data announcement.

โ€œOf the 639 cases in hospital with Covid, 27 are in Northland, 99 in Waitemata, 116 in Counties Manukau, and 99 in Auckland. 29 are in high dependency care. Of those in hospital in the Northern Region with Covid, 40 people are unvaccinated or not eligible, 9 are partially immunised, 67 are double vaccinated, 76 are boosted. The vaccination status of 139 cases is unknown.โ€

What caught my interest was the fact that the Ministry of Health did not know the vaccination status of 139 cases in the Northern Region. That is a full 42% of all cases.

In fact, since the realization a month ago that mRNA vaccination provides little or no protection against Omicron, the Ministry of Health’s daily briefings have suffered from a conspicuous absence of meaningful reports or discussion about the vaccination status of those hospitalized with Covid. This is presumably too embarrassing for the Ministry of Health worthies to mention.

Data Irregularities

Those of us who pour over the daily figures are also handicapped by a number of irregularities in reporting. Between March and April, the 12+ partially vaccinated group lost 13,117 people, but confusingly the 12+ fully vaccinated group lost 6,919 people with no explanation offered of where they disappeared to.

Sometimes the Ministry of Health’s cumulative case numbers are smaller than the previous day. For your information, cumulative totals have to increase every day by definition. Presumably, the deeply somnambulant group of reporters at the briefing failed to notice this, but for us data addicts these figures are deeply puzzling.

Do we wonder if perhaps one of the adverse effects of vaccination is a sort of amnesic condition that erodes the commitment to count?

This perception has been strengthened by reports from a number of countries overseas including the UK where some daily totals and vaccination status information was quietly dropped from reports when hospitalization rates among the vaccinated exceeded that of the unvaccinated.

In fact, the Ministry of Health’s reluctance is just an extension of previous practice. It has refused to institute mandatory reporting of adverse effects. This shows a continuing disinterest in accurately assessing the effects of the novel mRNA vaccine.

The Ministry of Health website provides a tantalising clue: 

โ€œwe cannot give detailed information about cases in your district, city, or town, as we must protect the privacy of the people concerned.โ€ 

A curious attitude towards our right to medical privacy considering that up until now we have had to openly prove our positive vaccination status in order to enter a restaurant or library.

Ministry of Health officials apparently canโ€™t keep track of the vaccination status of nearly half of hospitalisations despite our sophisticated NZ reporting and data tracking system that is often touted as world-beating (and has absorbed some of the $64 billion borrowed dollars the government has spent on the pandemic so far).

It doesnโ€™t stop there. Dr. Ashley Bloomfield announced that 30-40 percent of hospitalised Covid patients are there coincidentally. Their hospitalisation has nothing to do with Covid at all.

In saying this, he was directly contradicting another Ministry of Health official who announced last month that 75% of hospitalisations with Covid are unrelated to Covid.

As the sad Covid death toll rises (it has reached 426 over two years compared to 66,000 from all other causes), we are left wondering how many of the 426 deaths are actually due to Covid?

The Virus Within

Dr. McElnay, announcing her resignation, treated us to a special insight. One of her main challenges as Director of Public Health was โ€œMisinformationโ€ which she termed โ€œthe virus withinโ€.

I was not sure if she meant this was within the Ministry of Health, which would make a lot of sense to me, but she clarified the matter by hinting that this misinformation virus was coming to New Zealand from overseas. Since she announced she would be going overseas shortly, perhaps she is going to sort this out for us? I hope not.

The Ministry of Health public health department which McElnay has led is either too incompetent to properly read full scientific papers, or worse, really have lost the ability to count.

Dr. McElnay announced at the 1 pm briefing (26/11/21) that a study in Scotland had shown the Pfizer jab to be 90% effective against death for the Delta strain.

This is the sort of headline announcement that has cemented the publicโ€™s understanding that mRNA vaccination is not only very effective but also essential for everyone.

This leads people to erroneously identify unvaccinated persons as a source of risk to public health.ย This was not in fact a formal study but a letter to the editor of the journal which did indeed claim a 90% efficacy against death.

However, as is so often the case, the most interesting part of studies is to be found in the additional ‘supplementary’ documents (the part that few people read – and therefore the best place to bury data which you would prefer the media do not pick up on). This is what the supplementary material showed:

  • There were 74 deaths in the 40,233 unvaccinated people, and 127 deaths in the 62,246 vaccinated people.
  • This means that 0.18% of unvaccinated subjects died, and 0.2% of the vaccinated died (a larger percentage).

The vaccinated and unvaccinated cohorts were very similar in terms of demographics, comorbidities etc, so it is unclear as to how the authors justified their conclusions.

I guess if your results show that the vaccinated are ever so slightly more likely to die, you will need to make enough surreptitious data adjustments to end up with a result that will actually get you published in the current pro-vaccine climate.

I highly doubt that McElnay and her team had sufficiently investigated the supplementary PDF before making the announcement.

Time to Admit the True Figures

We come to the nub of the problem, for two years the government has been telling the population that the vaccine is safe and effective. Not so much telling us, but drumming it into our heads ad nauseum through an endless saturation, and certainly very costly, advertising campaign.

At this point, a change of gears would be quite worrying for a majority of New Zealanders who are cocooned in an illusory safety net constructed from a web of half truths.

Yesterday I noticed a disturbed government supporter insisting on FB that no one has ever been hospitalized with Covid who has been vaccinated. A measure of just how opaque the governmentโ€™s daily Podium of Truth is.

There is no doubt we have arrived at a moment of crisis.

Many people are waking up to the ineffectiveness of mRNA vaccination, but the Ministry of Health is not admitting that. The vast majority of us have been lulled into a comforting world where vaccination reduces the incidence and severity of Covid, against all evidence.

If we believe the governmentโ€”no matter what the severity of our infection, we will presume that vaccination lessened our symptoms. Thus for the trusting layman, the governmentโ€™s current advice cannot possibly be falsified, that is unless the government were to start reporting the statistics in a complete and unbiased fashion.

If the government continues to insist that boosters and masking will protect us stretching out into the future, as Dr. McElnay gaily announced on the eve of her departure, we may be both daunted and assured, but we will also be deceived.

The vaccine has been largely ineffective against Omicron, the implications of that truth need to be faced.

Response to Accusations of Misrepresentation of Facts Leading to Social Disharmony

Letter to: David Fisher, Senior Writer, New Zealand Herald

In response to: Your criticism of the Daily Telegraph NZ and Dr. Guy Hatchard

7th April 2022

Dear David

We havenโ€™t met, but a letter from yourself to the editor of the Daily Telegraph has been forwarded to me. In this letter, you say you are writing about โ€œdisinformation and misinformation relating to Covid-19โ€. You mention me as โ€œsomeone who commonly misrepresents factsโ€. You also want to know whether the DTNZ Editor feels I am โ€˜credibleโ€™ and whether I take the time to โ€˜verify my sourcesโ€™. Specifics and references are largely absent from your letter, but you do take issue with the use of the term โ€œexperimental jabโ€. I searched my computer this morning but couldnโ€™t find any occasion when I have used it. You also present something you refer to as โ€œfact-checked public health adviceโ€ as the gold standard that newspapers should follow. Finally you imply articles in the DTNZ, presumably including my own, โ€œhave been linked by security services and academics to social disharmonyโ€.

For several months now, I have been sending my press releases to your personal email. I have never heard back from you. You have until now never asked me any questions. Nevertheless thank you for asking your first, albeit to a third party. You describe yourself as โ€œUncovering stories that matter, asking hard-hitting questions of those in power, โ€ฆ.and providing Premium expert opinion and analysis.โ€ You are a Senior Writer at the Herald, so you do deserve a detailed reply.

Firstly, I try to reference my work to mainstream scientific publications. If you want to make criticisms, to maintain credibility I suggest that as far as possible you do the same and engage with specific content. I believe that open rational discussion, debate, criticism, experiment, analysis, theory, and speculation all play a vital role in the progress of scientific understanding. Seeking to close that down, or limiting who may take part, amounts to censorship, which I am sure as an experienced senior journalist you wish to avoid for the good of society. Transparency and participation are hallmarks of a civil society.

I am a 71 year old retired scientist. Having worked at one time in the genetic testing industry, I am aware that biotechnology has a chequered safety record which I have written and spoken about. I am also aware of the normal testing protocols for vaccines. Due to the pressure of time, these have not been followed during the development of mRNA vaccines. In particular, the investigation of secondary effects has not been completed, a stage of testing vital in the determination of safety. In this context, I do not find the use of the term โ€˜experimentalโ€™ to be inappropriate or disharmonious when describing the various Covid-19 vaccines.

I am aware of arguments advanced in the popular press that the vaccine has already been administered to billions of people in multiple countries and that this is tantamount to proof of an unprecedented level of safety. This argument has been advanced to justify government sponsored advertising describing the Pfizer vaccine as safe and effective. Pfizer itself admits to adverse effects, why shouldnโ€™t our government do so publicly? More importantly from a scientific standpoint, widespread use is insufficient to guarantee safety. As I am sure you are aware, the examples of false safety assumptions, based solely on availability, are too numerous to ignore. Paracetamol is widely used, but few people realise long term or excessive use damages the liver.

Your implied charge that discussion of Covid-19 safety is causing โ€œsocial disharmonyโ€ is hard to fathom. You tie this to the notion of โ€œfact-checked public health adviceโ€. Presumably you are referring to the need for the government to be our sole source of information. In 1990/91 I was invited by the Armenian Ministry of Health to help organise the treatment of PTSD after the massive earthquake in late 1989, in which over 25,000 people perished. This was still during the Soviet era, so I had the opportunity to observe first hand what happens to society when the government is your sole source of information. I remember vividly on some days wandering the streets for hours to find a shop with potatoes and bread to buy.

I also remember visiting the Armenian Theoretical Physics Institute. It was a curious quirk of the prescribed Soviet education system that students were shuffled towards specific narrow professions at an early age based on aptitude tests. The physics institute had some brilliant scientists, but the majority were square pegs in round holes. As the working day finished, misplaced โ€˜physicistsโ€™ surged towards the exit in order to pursue their real interests and earn hard cash from the black market.

Donโ€™t get me wrong, there were some useful benefits of surveillance and control as long as you were on the right side. As I was working for the government, I only had to ask out loud in my hotel room for assistance and the next day it miraculously appeared. Is this the future we aspire to in NZ? We havenโ€™t progressed that far yet and hopefully never will. I have tried asking the blinking red light on my home computer for assistance, but it hasnโ€™t materialised. Then again perhaps the security services you mention think I am on the wrong side. I am not on the wrong side of history though. Asking questions should never be demonised and mocked. As an experienced journalist you should know that. One of the first acts of the Nazi state was to censor Jewish scientists and lock up intellectuals in concetration camps. The unvaccinated can still contribute to science, in fact they provide a needed balance.

Am I angry? No. Anger is the invincible foe. Anger interferes with rational thought. Social conflict destroys the stability on which we all rely. Without the police and security services we could be in for a rocky ride. The Christchurch attacks taught us that. But equally, suppression of freedom of discussion and choice is a well worn path to social dysfunction and tyranny. A couple of days ago I was out shopping and a lady recognised me. She emigrated to NZ from Poland years ago, but the last two years have taken her back to her childhood experiences of Soviet repression. She expressed thanks for the freedom of discussion and expression available at the Hatchard Report and DTNZ. Do I seek regime change? No. I am old enough to know that if the leader is pushed out, they are often replaced by someone less agreeable. I believe in the power of knowledge. In the end, as Shakepeare said the โ€œtruth will outโ€. As an experienced journalist, I am sure you know your role is to seek it, not suppress it, to cite your sources without fear or favour.

For perspective, I watched a Monty Python episode last night about a truly happy kingdom in a valley far far away in the mountains. The most contented kingdom the world has ever known. It was ruled over by a wise old king called Otto. All his subjects flourished and were happy. There were no discontents or grumblers because wise King Otto had them all put to death along with the trade union leadersโ€ฆ.

Best wishes

Guy

The Joyless Psychology of the Pandemic

0

Have you noticed how the pandemic has been essentially joyless?

Joy resides in consciousness. Although our sensory experiences can provide a trigger, joy is an inner experience that relies on our alertness. Much of pharmaceutical medicine is geared to reduce alertness and suppress experience.

Sometimes painkillers are incorrectly prescribed as a means to hide symptoms rather than investigate the cause. You might be able to keep going, but your immune system will miss the necessary healing rest.

Curiously, the side effects of many modern medicines are often similar to the problems they are designed to treat. Prolonged use of morphine-like painkillers not only leads to addiction, but ultimately causes more pain.

Addiction is characterised by a loss of control or choiceโ€”our conscious capacity to choose is reduced. During 2021, deaths from opioid overdose ran at over an unprecedented 100,000 in the USA alone.

Impairment of consciousness is not limited to painkillers. Aย studyย by researchers in Massachusetts institutions including Harvard Medical School published a few days ago found that antibiotic use in mid life leads to cognitive impairment in later life.

Antidepressant use is associated with increased risk of suicide. Steroid use can lead to confusion and delirium. Blood pressure medication can be associated with depression and sleep disruption, and so on.

So have medical authorities earned the right to mandate pharmaceutical interventions and override personal medical choice?

mRNA vaccination exposes our physiology to the same toxic spike protein as Covid infection, in even greater quantities. No wonder that the vaccine has an alarming range of neurological adverse effects including some associated with the brain/physiology interface.

It is immediately obvious that our physiology is intimately connected to our consciousnessโ€”our sense of psychological well being and joy. The relationship between consciousness and physiology is delicately balanced and easily upset by medication. The common side effects of drugs result in a loss of control over everyday life.

Is Greater Control the Hidden Agenda of the Pandemic?

Do you spend time like me wondering how it happened that the government, media, the pharmaceutical industry, big business, and the medical establishment took common cause during the pandemic? What binds them together so closely? All of the parties to the pandemic have a mission statement to control the public:

  • The government wants to sway public opinion in their favour.
  • Mainstream media are busy helping them to mould public opinion.
  • Take a masters in business education, and a major focus is how to influence customer choice by any and all means.
  • The pharmaceutical business relies on a PR machine that reaches into and greases the wheels of every corner of society. This yearโ€™s Oscars were proudly sponsored by Pfizer for example.
  • Medical practice is intimately linked with pharmaceutical companies. There are gold standard prescriptions which doctors must follow. If they deviate, they may lose their licence to practice.

There is a certain immorality in the massive business of persuasion this involves. Jockeying for position during the pandemic, strange bedfellows have imagined that they share a common cause and acted to maximise each otherโ€™s financial, political, and professional advantage. As we have found out, it is a short step from persuasion to fear, misinformation, coercion, and even tyranny.

The practice of deception is inherently devoid of kindness and also devoid of joy. The closure of rational debate and the removal of legal liability has brought out the worst in the protagonists, who are acting like playground bullies, leading to draconian legislation removing human rights, media misinformation, and obscene pharmaceutical profits.

When it comes to getting ahead, donโ€™t rock the boat. A friend of ours is a radiologist, she was in the hospital canteen and overheard three doctors talking at the next table. They were telling each other that there was no way they would have their children vaccinated. They were worried about rates of myocarditis. So this is the joyless psychology of the pandemic: itโ€™s OK to inject someone elseโ€™s children with an experimental gene therapy. If you speak up you might lose your job, so mums the word.

New Zealand Epidemiologists Blow Their Own Trumpet

The long term effects of mRNA vaccination are still unknown, but an article in the UK Guardian newspaper yesterday entitled โ€œNew Zealandโ€™s Covid strategy was one of the worldโ€™s most successful โ€“ what can we learn from it?โ€ by NZ epidemiologists Michael Baker and Nick Wilson spelled out how important it is to blow your own trumpet during the pandemic. They emphasised New Zealandโ€™s achievements including:

  • leadership that listens to the science
  • use of the precautionary principle in the face of uncertainty
  • creating legacy benefits for our healthcare and public health systems
  • the team of five million building consensus
  • the role of government control, including better surveillance

I realise that the Guardian is a long way removed from New Zealand and may not be in position to evaluate articles submitted from the antipodes. I thought a small amount of translation may help them.

Leadership That Listens to The Science

The best approach is to fund science directly through Te Punaha Matatini so that they can tell the government what they want to hear such as: herd immunity and vaccine adverse effects are a conspiracy theory.

Use of the precautionary principle in the face of uncertainty

Ignore Pfizerโ€™s safety guidelines, our government insisted that even if seriously injured by the first dose, you must still get the second jab.

Creating legacy benefits for our healthcare and public health systems

Where are these actually? The government spent $64 billion of borrowed money on its pandemic response but couldnโ€™t spare any money to upgrade hospitals. It also sacked highly qualified unvaccinated staff.

The team of five million building consensus

If you didnโ€™t want to be vaccinated, you faced loss of employment and social isolation.

The role of government control, including better surveillance

Need I say anything about this?

Baker and Wilson didnโ€™t mention the 100โ€™s of millions of dollars spent propping up uncritcal media, the unprecedented level of mRNA vaccine adverse effects running at 30-50 times higher than before, or the loss of small businesses and our tourism industry.

The psychology of the pandemic requires a lot of trumpet blowing all round, but not a lot of listening. Telling us that it has all been for the greater good, when actually it is an experiment with an unknown outcome, is nonsense. It has left us all shell shocked and facing an uncertain future. The government is still crudely stoking the fear factor full steam with saturation advertising promising dreadful variants and dire consequences for the unboosted. Not a single politician has called for rational debate.

So who will we vote for in 2023? Well we do not know, it will be Hobsonโ€™s Choice. All parties have worked together as the harbingers of doom and gloom helping blanket the nation with the joyless propaganda of fear. But we can change the narrative, we donโ€™t have to follow blindly. It is up to us.